Key takeaways
- Population health and ethics is 12.5% of the blueprint, which is about 19 of 150 questions. Ethical issues also turn up inside stems from other domains.
- Adults are presumed to have capacity. A competent adult can refuse any treatment, and you should follow a valid advance care directive.
- Australia has no single age of medical consent. A mature minor can consent, and in South Australia people aged 16 or over consent as adults.
- You can break confidentiality only with consent, where the law requires or permits it, or to lessen or prevent a serious threat.
- For a treating doctor, the trigger for an Ahpra notification is a substantial risk of harm to the public. Sexual misconduct has a lower threshold.
- Prevalence changes PPV and NPV but not sensitivity or specificity. NNT = 1 ÷ absolute risk reduction.
AMC ethics questions look easy until you sit them. The stem is short, every option sounds reasonable, and the best answer depends on Australian law and the Medical Board's code of conduct rather than on what you learnt at home. Add a population health AMC MCQ that asks for a positive predictive value in 84 seconds, and this 12.5% of the exam suddenly feels much bigger.
This guide sets out the rules the AMC expects you to apply. It then works through the biostatistics and screening principles step by step, and every calculation has been checked.
How AMC ethics questions and population health items are examined
The AMC's MCQ specifications describe this patient group in four parts:
- Population health: strategies that improve the health of targeted populations, including screening.
- Ethics: professional behaviour, including boundaries, confidentiality and informed consent.
- Law: the regulations that govern Australian health care.
- Across settings: population health concepts can come up in any clinical setting.
Most stems end with "What is the most appropriate action?" and two or three of the options are usually lawful. The best answer protects the patient, respects their autonomy and takes the least drastic lawful path.
Exam tip: If two options both look ethical, pick the one that involves talking to the patient first, such as "discuss" or "seek consent to share". Acting on your own is only right in an emergency or when you have a legal duty.
Consent: the rules behind most AMC ethics questions
Good medical practice: a code of conduct for doctors in Australia requires informed consent before any examination, investigation or treatment, except in an emergency. It also requires consent before patients are involved in teaching or research. You must give the information in a form the patient can understand, and that includes your fees.
Valid consent has four elements: capacity, voluntariness, information and specificity. Specificity means consent to a diagnostic laparoscopy does not cover a hysterectomy you find convenient to do at the same time.
The Australian standard for what to disclose comes from Rogers v Whitaker (1992). A risk is material if a reasonable person in the patient's position would attach significance to it, or if you know this particular patient would.
Capacity and substitute decisions
Capacity is presumed, and it applies to one decision at one time. The patient must be able to:
- understand the relevant information
- retain it
- weigh it
- communicate a choice.
An unwise decision does not prove incapacity. If capacity fluctuates, for example in delirium or hypoglycaemia, treat the cause and reassess.
If the patient lacks capacity, consent comes from a substitute decision-maker, who must take any advance care directive into account. Who that person is depends on state guardianship law. It is usually an appointed guardian, then a spouse or partner, a carer, or a close relative or friend. In a genuine emergency with no directive and no substitute available, give only the treatment needed to save life or prevent serious harm.
| Scenario in the stem | Best first step | Common wrong answer |
|---|---|---|
| Competent adult Jehovah's Witness refuses transfusion | Confirm an informed, voluntary refusal in private; offer blood-sparing options; document | Seek a court order to transfuse |
| Unconscious adult after a crash, no family reachable | Treat the emergency, giving only what is necessary | Wait for a relative to consent |
| Delirious adult refusing antibiotics | Assess capacity for this decision; involve the substitute; treat the cause | Accept the refusal because the patient is an adult |
| Valid advance care directive refusing intubation | Follow the directive | Intubate because the family asks you to |
Minors: Gillick competence and the mature minor in Australia
In Marion's case (1992), the High Court adopted the Gillick principle. A minor can consent once they have enough understanding and intelligence to fully understand what is proposed. The code asks you to put the young person's interests first, consider their capacity, and encourage them to involve their parents where appropriate.
- South Australia: under the Consent to Medical Treatment and Palliative Care Act 1995, a person aged 16 or over can make decisions about their own treatment as an adult. A child under 16 can consent if you believe they understand the nature, consequences and risks, and the treatment is in their best interests. Another doctor who has examined the child must support that opinion in writing.
- New South Wales: the NSW Health consent manual sets out three bands.
- At 16–17, the young person's own consent is usually enough.
- At 14–15, you should also seek a parent's consent unless the young person objects.
- At 13 and under, you need a parent's consent.
- Refusal: a court can override a minor's refusal of life-saving treatment. Being competent to consent does not always mean being competent to refuse.
- Emergencies: state law lets you treat a child without consent to save their life or prevent serious damage to their health. That includes giving blood when the parents object.
- Procedures outside parental power: some procedures, such as non-therapeutic sterilisation, need court or tribunal approval. That was the issue in Marion's case.
A 15-year-old girl attends a general practice alone and asks for the oral contraceptive pill. Her boyfriend is 16 and they have been together for six months. She asks you not to tell her parents. She explains the benefits, the side effects and the need to take the pill daily, and she knows it does not prevent sexually transmitted infections. There are no features of coercion or abuse. What is the most appropriate action?
- Decline to prescribe until a parent attends and consents
- Prescribe the pill, then phone her mother to let her know
- Treat her as a mature minor and prescribe with STI advice
- Refer her to a sexual health clinic instead of prescribing
- Notify child protection services because she is under 16
Show answer and explanation
Answer: C. She shows mature-minor understanding and there are no warning signs of exploitation. Prescribe, keep her information confidential, encourage her to involve a parent, and advise her on condoms and STI testing.
- A is wrong because a competent minor doesn't need a parent's consent.
- B is wrong because it breaches her confidentiality.
- D is wrong because it delays care you can give yourself.
- E is wrong because a consensual relationship with a similar-aged peer doesn't meet the reporting threshold on its own.
Always ask about age gap and coercion, because either can change the answer.
Choose a pass for AMC MCQ
Practise Population Health Ethics and every other blueprint domain. One exam per pass, from $30, no auto-renewal.
Confidentiality and its exceptions
The code says you must treat patient information as confidential unless release is required or permitted by law. You should access a record only when you have a legitimate need, so looking up a neighbour's record out of curiosity is a breach.
| Exception | Typical stem | What to do |
|---|---|---|
| Consent | Insurer or employer requests a report | Get written consent and disclose only what is relevant |
| Required by law | Notifiable disease, child abuse, subpoena, Ahpra notification | Disclose to the authority as required, and no more |
| Serious threat | Credible plan to harm an identified person | Tell those who can prevent the harm, such as police |
| Shared care | Referral, multidisciplinary team | Share what the patient's care needs |
The serious-threat exception comes from the Privacy Act. You must reasonably believe the disclosure is necessary to lessen or prevent a serious threat to life, health or safety, and getting consent must be unreasonable or impracticable. The threat does not have to be imminent, but disclosure that is merely helpful or convenient is not allowed.
Parents of adult children and spouses have no automatic right to a patient's information. You can always listen to their concerns, but you can't disclose anything without the patient's consent.
Use qualified interpreters rather than family. Private practitioners can use TIS National's free service for Medicare-rebateable care by calling the priority line on 1300 131 450.
Under Austroads' Assessing Fitness to Drive standards, the driver is responsible for reporting a condition to the licensing authority. After a first seizure, your duty is to advise the patient not to drive, explain the standard and document your advice. Consider notifying the authority only if they keep driving against your advice.
Mandatory reporting: children at risk and impaired practitioners
Child abuse and neglect
Doctors are mandatory reporters in every state and territory, and in the Northern Territory the duty applies to everyone. The legal threshold differs by jurisdiction:
- Reasonable suspicion: NSW, Queensland and South Australia.
- Belief on reasonable grounds: the ACT, the Northern Territory, Victoria and Western Australia.
- Either: Tasmania.
No jurisdiction requires you to be certain. The types of abuse covered also vary. Victoria covers physical injury and sexual abuse, while NSW and Tasmania also cover neglect, emotional harm and exposure to family violence.
Exam tip: Watch for an injury that doesn't match the history, a delay in seeking care, or bruising in a baby who isn't yet mobile. The answer is to report to child protection and keep the child safe. Don't confront the parents and don't wait for proof.
Ahpra mandatory notifications about practitioners
Since 1 March 2020 the rules have been designed so that practitioners can seek help for their own health without fear. Ahpra notes that a health issue rarely needs a mandatory notification.
| Concern | Treating practitioner notifies when… | Non-treating practitioner or employer notifies when… |
|---|---|---|
| Impairment | there is a substantial risk of harm to the public | the impairment places the public at risk of substantial harm |
| Intoxication while practising | there is a substantial risk of harm to the public | the practitioner practises while intoxicated |
| Significant departure from professional standards | there is a substantial risk of harm to the public | the departure places the public at risk of harm |
| Sexual misconduct | there is a past, current or future risk (lower threshold) | the practitioner engages in sexual misconduct connected to practice |
You need a reasonable belief before you notify, not rumour, and you must notify as soon as practicable. Treating practitioners in Western Australia are exempt.
You are the GP of a 48-year-old orthopaedic surgeon who tells you she has alcohol use disorder. Two weeks ago she stopped operating of her own accord and started treatment with an addiction specialist. She has never practised while intoxicated and is engaged with her recovery. What is the most appropriate action regarding notification?
- Notify Ahpra now, as alcohol use disorder is an impairment
- Inform her hospital's director of medical services
- Advise her that she must self-report to the Medical Board
- Notify Ahpra only if she agrees that you should do so
- Continue treatment; no mandatory notification is required
Show answer and explanation
Answer: E. As her treating practitioner, you must notify only if she poses a substantial risk of harm to the public. She is not operating and is engaged in treatment, so that risk isn't present. Reassess if things change.
- A is wrong because having an impairment alone doesn't meet the threshold.
- B is wrong because it breaches her confidentiality.
- C is wrong because it misstates her obligations.
- D is wrong because a statutory duty never depends on the practitioner's agreement.
Boundaries, open disclosure and end-of-life care
Professional boundaries
Never use your professional position to pursue a sexual or exploitative relationship with a patient.
- Avoid treating family members or close friends.
- Decline any gift from industry that is more than trivial in value.
- You may hold a conscientious objection, but you must tell the patient and must not use it to block their access to lawful care, such as contraception.
- Culturally safe care for Aboriginal and Torres Strait Islander patients is part of good medical practice.
Open disclosure
The Australian Open Disclosure Framework applies when an adverse event harms a patient. It has five elements:
- an apology or expression of regret that includes the words "I am sorry" or "we are sorry"
- a factual explanation of what happened
- an opportunity for the patient, their family and carers to relate their experience
- a discussion of the possible consequences
- the steps being taken to manage the event and prevent it happening again.
Every Australian jurisdiction has laws that protect apologies in certain legal settings. Disclosure starts early with the facts you know. Don't wait for the incident review.
End of life
The code says you have no duty to prolong life at all cost, but you must relieve distress. Patients may refuse treatment or ask for it to be withdrawn.
- Advance care directives: follow a valid directive that clearly applies, even if the family disagrees.
- Withholding and withdrawing treatment: these are ethically equivalent.
- Double effect: opioids titrated to relieve symptoms are lawful even if they may shorten life.
- Voluntary assisted dying: each state and territory has its own Act with strict criteria. The ACT's Act, for example, requires the person to be 18 or older and to have decision-making capacity at every stage, and mental illness alone does not qualify.
Choose a pass for AMC MCQ
Basic, Pro and Premium passes for 1, 3 or 6 months. One exam per pass, from $30, no auto-renewal.
Population health AMC MCQ topics: study designs and key terms
| Design | Direction | Main measure | Key weakness |
|---|---|---|---|
| Randomised controlled trial | Intervention allocated, followed forward | RR, ARR, NNT | Cost; generalisability |
| Cohort | Exposure → outcome | Incidence, relative risk | Loss to follow-up; slow for rare disease |
| Case–control | Outcome → past exposure | Odds ratio | Recall and selection bias |
| Cross-sectional | One point in time | Prevalence | Cannot show temporality |
| Ecological | Groups, not individuals | Correlation | Ecological fallacy |
- Prevalence ≈ incidence × duration. So a treatment that prolongs life without curing the disease raises prevalence.
- Confounding: a third factor linked to both the exposure and the outcome. You control it with randomisation, matching, stratification or multivariable analysis. A bigger sample doesn't fix bias.
- Type I error (α): a false positive, usually set at 0.05.
- Type II error (β): a false negative. Power = 1 − β, often 80%.
- 95% confidence intervals: a ratio is not significant if its interval includes 1, and a difference is not significant if its interval includes 0.
Biostatistics with worked calculations
Draw the 2×2 table the same way every time, with disease status across the top and the test result down the side. That gives you true positives (a), false positives (b), false negatives (c) and true negatives (d).
- Sensitivity = a ÷ (a + c). A sensitive test, when negative, rules the disease out (SnNout).
- Specificity = d ÷ (b + d). A specific test, when positive, rules the disease in (SpPin).
- PPV = a ÷ (a + b).
- NPV = d ÷ (c + d).
- LR+ = sensitivity ÷ (1 − specificity).
- LR− = (1 − sensitivity) ÷ specificity.
Worked example: prevalence changes PPV
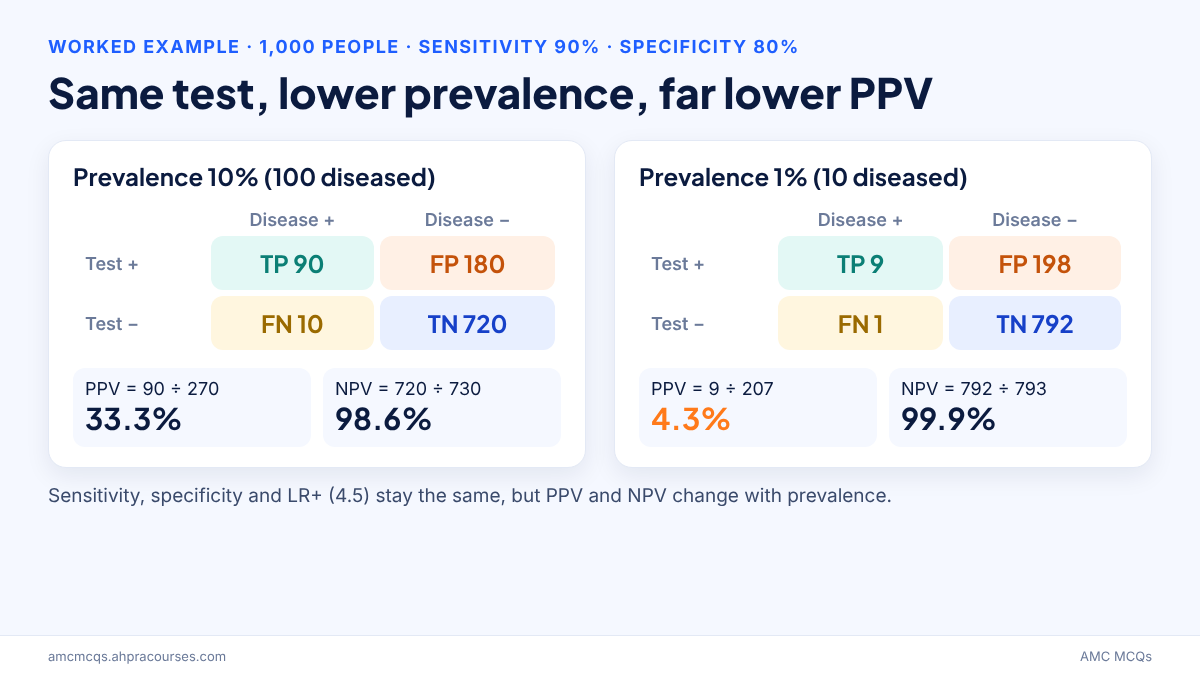
A test with 90% sensitivity and 80% specificity is used on 1,000 people, and the prevalence is 10%.
- Of the 100 people with the disease, 90 test positive (true positives) and 10 test negative (false negatives).
- Of the 900 people without the disease, 720 test negative (true negatives) and 180 test positive (false positives).
- PPV = 90 ÷ 270 = 33.3%.
- NPV = 720 ÷ 730 = 98.6%.
Now use the same test at 1% prevalence. You get 9 true positives and 198 false positives, so the PPV falls to 9 ÷ 207 = 4.3%, and the NPV rises to 99.9%. The likelihood ratios stay the same at both prevalences: LR+ = 0.90 ÷ 0.20 = 4.5 and LR− = 0.10 ÷ 0.80 = 0.125.
Risk, NNT and NNH
Suppose a stroke occurs in 10% of controls (the control event rate, CER) and 6% of treated patients (the experimental event rate, EER).
- RR = 0.06 ÷ 0.10 = 0.6
- ARR = 10% − 6% = 4%
- RRR = 0.04 ÷ 0.10 = 40%
- NNT = 1 ÷ 0.04 = 25
If bleeding occurs in 4% of treated patients and 2% of controls, then NNH = 1 ÷ 0.02 = 50. Round an NNT up to the next whole person.
In a case–control study, suppose 60 of 100 cases and 30 of 100 controls were exposed. Then OR = (60 × 70) ÷ (40 × 30) = 3.5. You can't calculate a relative risk from a case–control design.
A rapid antigen test is evaluated in 1,000 adults. Of the 200 adults with the infection on PCR, 160 test positive. Of the 800 adults without the infection, 720 test negative. What is the positive predictive value of the rapid test?
- 80.0%
- 66.7%
- 90.0%
- 94.7%
- 33.3%
Show answer and explanation
Answer: B. There are 160 true positives and 80 false positives, so PPV = 160 ÷ 240 = 66.7%.
- A is the sensitivity (160 ÷ 200).
- C is the specificity (720 ÷ 800).
- D is the NPV (720 ÷ 760).
- E is false positives divided by all positives (80 ÷ 240), a common slip.
In a randomised trial, 20% of patients taking placebo and 15% of patients receiving treatment had a cardiovascular event over five years. How many patients must be treated for five years to prevent one event?
- 5
- 4
- 25
- 20
- 7
Show answer and explanation
Answer: D. ARR = 20% − 15% = 0.05, so NNT = 1 ÷ 0.05 = 20.
- A is the ARR written as a percentage.
- B is 1 ÷ RRR, where the RRR is 25%.
- C is the RRR misread as the NNT.
- E is about 1 ÷ 0.15, which uses the event rate in the treatment group instead of the difference between groups.
Screening principles: Wilson–Jungner and Australian programs
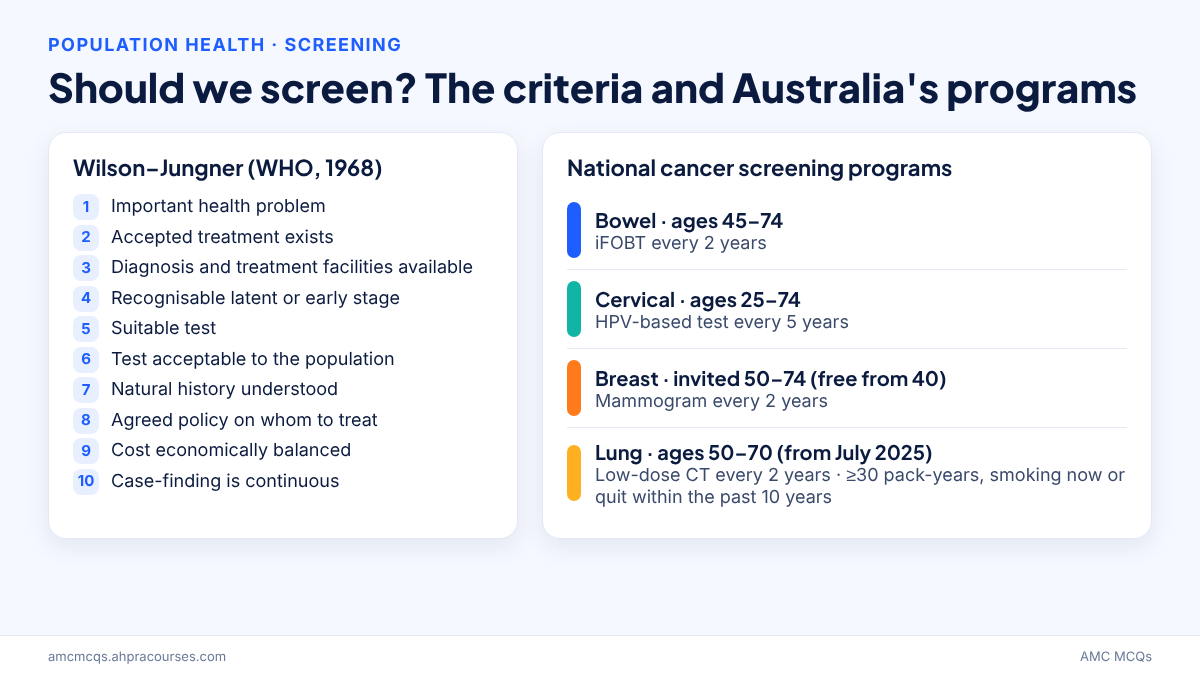
The Wilson and Jungner criteria (WHO, 1968) set out when screening is justified:
- The condition is an important health problem.
- There is an accepted treatment.
- Facilities for diagnosis and treatment are available.
- There is a recognisable latent or early stage.
- A suitable test exists.
- The test is acceptable to the population.
- The natural history of the condition is understood.
- There is an agreed policy on whom to treat.
- The cost is economically balanced.
- Case-finding is a continuing process.
Australia's Population Based Screening Framework adapts these criteria and adds two more: high-quality evidence that benefits outweigh harms, and program requirements such as a register, informed choice and equity of access.
Watch for the biases that flatter screening:
- Lead-time bias: survival looks longer only because the diagnosis came earlier.
- Length-time bias: screening picks up more slow-growing disease.
- Overdiagnosis: screening finds disease that would never have caused harm.
The proof that a screening program works is a fall in disease-specific mortality.
| Program | Who | Test and interval |
|---|---|---|
| National Bowel Cancer Screening Program | Ages 45–74 | iFOBT every 2 years |
| National Cervical Screening Program | Ages 25–74 | HPV-based cervical screening test every 5 years |
| BreastScreen Australia | Invited at 50–74; free from 40 | Mammogram every 2 years |
| National Lung Cancer Screening Program (from July 2025) | Ages 50–70, no symptoms, ≥30 pack-years, still smoking or quit within the past 10 years | Low-dose CT every 2 years |
Australia has no national prostate screening program. If an asymptomatic man asks for a PSA test, discuss the benefits and harms with him before testing.
Common traps in AMC ethics questions, and how to practise
- Applying another country's law, such as the UK Mental Capacity Act, or assuming the family can consent for an adult.
- Breaking confidentiality before you have talked to the patient.
- Treating a refusal you disagree with as evidence of incapacity.
- Notifying Ahpra about a colleague who is in treatment and has already changed how they practise.
- Using the relative risk reduction to calculate an NNT.
Because our bank is blueprint-weighted, about one in eight questions is population health and ethics. Every explanation covers all five options.
- Do short timed blocks at 84 seconds per question in the question bank.
- Write a one-line rule for each mistake.
- Sketch a 2×2 table on the exam whiteboard every time you get a test-accuracy question.
Pair this guide with:
- Australian guidelines for the AMC MCQ
- the population health and ethics MCQ hub
- AMC MCQ high yield topics
- our AMC MCQ study plan
- the AMC MCQ exam guide.
Sit a timed AMC MCQ mock exam
Blueprint-weighted questions under exam timing, then a breakdown of your result by domain.
Frequently asked questions
How many ethics and population health questions are in the AMC MCQ?
About 19 of the 150 questions, because the domain makes up 12.5% of the blueprint. Ethical and legal issues also appear in questions from other domains.
Can a 15-year-old consent to treatment in Australia without a parent?
Yes, if they are a mature minor who understands the nature, consequences and risks of the treatment. In South Australia, a child under 16 can consent only with a second doctor's written support.
When can a doctor break confidentiality in Australia?
With consent, where a law requires or permits it, or where disclosure is necessary to lessen or prevent a serious threat to someone's life, health or safety and getting consent is unreasonable or impracticable.
What are the four grounds for an Ahpra mandatory notification?
Impairment, intoxication while practising, a significant departure from accepted professional standards, and sexual misconduct. For treating practitioners, the threshold for the first three is a substantial risk of harm to the public.
Do I need to memorise biostatistics formulas for the AMC MCQ?
Yes. No formula sheet is provided, but you get a whiteboard and pen to sketch a 2×2 table.