Key takeaways
- Women's health is 12.5% of the blueprint, which is about 19 of 150 questions.
- Cervical screening is a 5-yearly HPV test from 25 to 74, with self-collection open to everyone eligible. HPV 16/18 means direct colposcopy.
- Vaccines in each pregnancy: pertussis (dTpa) ideally at 20–32 weeks, RSV (Abrysvo) from 28 weeks, preferably 28–36 weeks, and influenza at any stage.
- Rh D-negative women: 625 IU anti-D at 28 and 34 weeks, and after sensitising events within 72 hours.
- Aspirin 150 mg at night, started before 16 weeks, for women at high risk of pre-eclampsia. Severe hypertension is 160/110 mmHg or above.
Women's health, meaning obstetrics and gynaecology, makes up 12.5% of the AMC CAT MCQ Examination blueprint. That is about 19 questions in a 150-item exam. AMC obstetrics and gynaecology MCQ items lean heavily on Australian programs and statements, such as the National Cervical Screening Program, the Immunisation Handbook pregnancy schedule, RhD prophylaxis and SOMANZ hypertension guidance. That makes it one of the most learnable domains if you revise the right numbers.
This hub covers antenatal care, pregnancy complications, labour and the postpartum period, early pregnancy and gynaecology. Each section focuses on what Australian guidance says today.
How AMC obstetrics and gynaecology MCQ questions are examined
Women's health items use the standard single best answer format and test all three AMC clinician tasks. Typical stems include:
- Antenatal care: a booking visit or routine review where you choose the test, vaccine or supplement due at that gestation.
- Acute obstetrics: bleeding, hypertension, reduced fetal movements or postpartum deterioration, where the question is the immediate next step.
- Early pregnancy: pain or bleeding with a positive pregnancy test, where the stem tests whether you can exclude ectopic pregnancy safely.
- Gynaecology and sexual health: a screening result to act on, a menstrual problem to investigate, or a contraception choice.
Gestational age is the most important number in every obstetric stem. Read it first, then work out which tests, vaccines and decisions apply at that point.
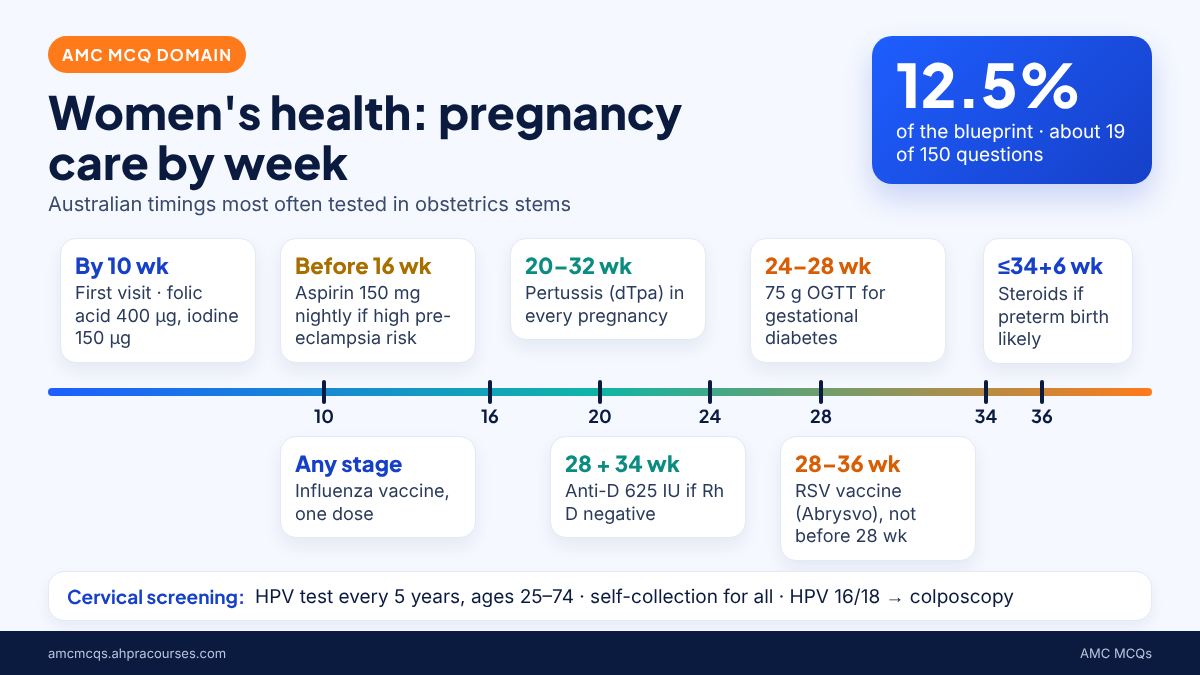
Antenatal care in Australia
The first antenatal visit
The RACGP recommends the first antenatal visit within the first 10 weeks of pregnancy. Offer the following:
| Area | What to offer |
|---|---|
| Blood tests | Full blood count, blood group and antibodies, hepatitis B, hepatitis C, HIV, syphilis, rubella immunity |
| Urine | Culture for asymptomatic bacteriuria; check for proteinuria |
| Sexual health | Chlamydia testing for women under 30 |
| Risk screening | Blood pressure, BMI, smoking, family violence (asked only when alone), depression (EPDS), pre-eclampsia and diabetes risk |
| Ultrasound | Dating scan if dates are uncertain; information on all prenatal screening options for chromosomal conditions, regardless of age |
Supplements
- Folic acid: 400 micrograms daily from 1 month before conception through the first 3 months. Use 5 mg daily if risk is higher, for example with anticonvulsant use, pre-existing diabetes, a previous neural tube defect or BMI over 30.
- Iodine: 150 micrograms daily throughout pregnancy, except in women with Graves' disease.
- Calcium: at least 1 g daily for women at high risk of pre-eclampsia with low dietary intake.
- High-dose vitamins A, C and E: not recommended.
Vaccination in pregnancy
| Vaccine | Timing (Australian Immunisation Handbook) |
|---|---|
| Pertussis (dTpa) | One dose in each pregnancy, ideally at 20–32 weeks |
| Influenza | One dose at any stage of pregnancy |
| RSV (Abrysvo only) | One dose from 28 weeks, preferably 28 to the end of 36 weeks; not before 28 weeks |
Live vaccines such as MMR and varicella are contraindicated in pregnancy. A rubella non-immune woman is vaccinated postnatally.
Rh D immunoglobulin (anti-D)
Australian guidance for Rh D-negative women without preformed anti-D:
- Routine prophylaxis: 625 IU at 28 weeks (after the antibody screen is taken) and 625 IU at 34 weeks.
- Sensitising events in the first 12 weeks (miscarriage, ectopic, molar pregnancy, termination after 10 weeks): 250 IU.
- Sensitising events after 12+6 weeks (antepartum haemorrhage, abdominal trauma, external cephalic version): 625 IU, with fetomaternal haemorrhage quantified after 20 weeks.
- Timing: as soon as practical within 72 hours. If that is missed, give up to 10 days after the event.
- After birth: 625 IU if the baby is Rh D positive.
Routine anti-D is not supported for termination before 10 weeks. Candidates often lose this mark by giving anti-D for every early loss.
Medical complications of pregnancy
Gestational diabetes
The routine test is a 75 g two-hour OGTT at 24–28 weeks. Women with risk factors should have an HbA1c in the first trimester. Those with previous gestational diabetes, or an early HbA1c of 6.0–6.4% (42–47 mmol/mol), should have an OGTT before 20 weeks, ideally at 10–14 weeks. An HbA1c of 6.5% or more, fasting glucose of 7.0 mmol/L or more, or a 2-hour value of 11.1 mmol/L or more at any gestation indicates overt diabetes in pregnancy.
The ADIPS 2025 consensus raised the diagnostic thresholds for gestational diabetes. One or more of the following now confirms the diagnosis:
- fasting glucose 5.3–6.9 mmol/L
- 1-hour glucose 10.6 mmol/L or more
- 2-hour glucose 9.0–11.0 mmol/L
These replace the earlier 5.1, 10.0 and 8.5 mmol/L cut-offs. Services are moving to the new thresholds at different speeds, so read the values in the stem carefully. A clearly diabetic result is unambiguous under either set.
Hypertensive disorders of pregnancy
The SOMANZ 2023 guideline is the Australian reference. The core decisions are:
- Prevention: aspirin 150 mg daily, ideally at night, started before 16 weeks for women at high risk. It may be stopped between 34 weeks and birth. Universal aspirin for low-risk first pregnancies is not recommended.
- Stable hypertension: labetalol, methyldopa or nifedipine as first-line, with the choice individualised.
- Severe hypertension (160/110 mmHg or above): an emergency. Use short-acting agents, such as IV hydralazine, IV labetalol or oral immediate-release nifedipine, and treat to below 160/110.
- Eclampsia prevention: magnesium sulfate, 4 g IV loading dose, then 1 g per hour, continued for 24 hours.
- Timing of birth: plan birth for pre-eclampsia at 37 weeks or later. Before 37 weeks, decide on maternal and fetal stability, and deliver at any gestation if the mother deteriorates.
- After birth: review within 1 week of discharge. Women with pre-eclampsia carry long-term cardiovascular risk, so they need ongoing follow-up.
Other medical problems in pregnancy
Cystitis in pregnancy is treated with nitrofurantoin 100 mg 6-hourly for 5 days (send a urine culture first and avoid nitrofurantoin close to delivery), and asymptomatic bacteriuria is always treated. Also revise thyroid disease (check TSH if risk factors are present), VTE risk assessment, anaemia, and the safety of common drugs in pregnancy and breastfeeding.
Try AMC MCQ practice questions free
Create a free account and answer sample questions with full explanations before you buy a pass.
Labour, birth and the postpartum period
Threatened preterm birth
- Antenatal corticosteroids: recommended when preterm birth is planned or expected within 7 days at up to 34 weeks and 6 days. The ideal timing is within 48 hours of birth. The regimen is betamethasone 11.4 mg IM, two doses 24 hours apart.
- Magnesium sulfate for fetal neuroprotection: recommended when birth is likely before 30 weeks. Between 30 and 34 weeks the decision is individualised.
Postpartum haemorrhage
Primary PPH is blood loss of 500 mL or more within 24 hours of birth. Severe PPH is 1,000 mL or more. Think of the 4 Ts: tone (70–80% of cases), trauma, tissue and thrombin.
| Step | Action (Queensland Health) |
|---|---|
| Call for help and assess | Fundal massage, lie flat, oxygen, two large-bore IV lines, bloods, measure loss |
| First uterotonic | Oxytocin 5 IU IV over 1–2 minutes (10 IU IM if no IV access) |
| Further uterotonics | Oxytocin infusion; ergometrine (avoid in hypertension); misoprostol |
| Antifibrinolytic | Tranexamic acid 1 g IV over 10 minutes, ideally within 3 hours; repeat once if needed |
| Escalation | Bimanual compression, balloon tamponade, theatre; activate the massive haemorrhage protocol |
Perinatal mental health
Screen with the Edinburgh Postnatal Depression Scale at the first visit, at least once later in pregnancy and after birth. Distinguish the baby blues (first days, self-limiting) from postnatal depression and from postpartum psychosis, which is a psychiatric emergency needing same-day assessment. For more on this, see the mental health hub.
Early pregnancy problems
Bleeding or pain in early pregnancy needs a quantitative β-hCG and a transvaginal ultrasound to locate the pregnancy. An unstable patient with a positive pregnancy test and abdominal pain has a ruptured ectopic pregnancy until proven otherwise. Resuscitate and take her straight to theatre. A pregnancy of unknown location in a stable patient is followed with serial hCG levels and repeat ultrasound.
Early medical abortion with mifepristone and misoprostol (MS-2 Step) is approved in Australia up to 63 days of gestation. Since 2023, any registered medical practitioner can prescribe it without additional certification, and nurse practitioners and endorsed midwives may also prescribe. Ultrasound helps confirm gestation and exclude ectopic pregnancy. State laws on later abortion differ, so stems usually focus on early care.
Gynaecology and sexual health
National Cervical Screening Program
Asymptomatic women and people with a cervix aged 25–74 have an HPV-based Cervical Screening Test every 5 years. Self-collection is offered to everyone eligible, has the same accuracy for HPV testing as a clinician-collected sample, and is safe in pregnancy.
| Result | Next step |
|---|---|
| HPV not detected | Routine screening in 5 years |
| HPV 16/18 detected | Refer directly for colposcopy |
| HPV (not 16/18) detected | Liquid-based cytology to set risk. A self-collected sample means returning for a clinician-collected LBC |
| Intermediate risk | Repeat HPV test in 12 months; direct colposcopy if 50 or older, Aboriginal and/or Torres Strait Islander, or 2 or more years overdue |
| Exit test at 70–74 | Discharge if HPV not detected; colposcopy if any HPV is detected |
| Abnormal bleeding or suspicious cervix | Diagnostic pathway with a co-test (HPV plus LBC), not screening |
After treatment for HSIL, test of cure is an annual HPV test starting 12 months after treatment. The patient returns to routine screening after two consecutive negative results.
Abnormal uterine bleeding and postmenopausal bleeding
Assess heavy menstrual bleeding for anaemia, structural causes and coagulopathy. Postmenopausal bleeding is endometrial cancer until proven otherwise. Investigate with transvaginal ultrasound and endometrial sampling as indicated. Unexplained bleeding on menopausal hormone therapy after the first 6 months also needs investigation.
Polycystic ovary syndrome
The 2023 International PCOS Guideline, led from Australia, diagnoses adults with at least two of hyperandrogenism, ovulatory dysfunction and polycystic ovarian morphology. AMH can replace ultrasound for morphology in adults. Ultrasound and AMH are not used in adolescents. The guideline's management points:
- lifestyle support for everyone
- the combined pill for irregular cycles or hirsutism
- metformin for metabolic features
- letrozole as first-line ovulation induction
Contraception and emergency contraception
Long-acting reversible contraception (implant and IUDs) is the most effective option and suits most women, including adolescents and nulliparous women. For emergency contraception:
- Copper IUD: within 120 hours (5 days). This is the most effective option, and it continues as contraception afterwards.
- Ulipristal acetate: up to 5 days. It is more effective than levonorgestrel, but hormonal contraception should be delayed for 5 days afterwards.
- Levonorgestrel: as soon as possible, up to 4 days. A double dose is recommended over 70 kg or BMI over 26.
Menopause
Menopausal hormone therapy is the most effective treatment for vasomotor symptoms. A woman with a uterus needs a progestogen to protect the endometrium, but a woman after hysterectomy does not. Transdermal oestrogen carries less VTE risk than oral, and it suits women with migraine, VTE risk or liver disease. Breast cancer risk is linked mainly to combined therapy and rises with duration.
Common traps for IMGs in women's health
- Old cervical screening rules: 3-yearly Pap smears from 18 or 21 are not Australian practice.
- Wrong pertussis timing: dTpa is given in every pregnancy, ideally 20–32 weeks, even if given in a recent pregnancy.
- Early RSV vaccine: Abrysvo is not given before 28 weeks.
- Anti-D overuse: not routine for termination before 10 weeks; 250 IU, not 625 IU, for events in the first 12 weeks.
- Aspirin dose: Australian guidance uses 150 mg, not 75 mg, started before 16 weeks.
- Skipping hCG: every woman of reproductive age with pain or bleeding needs a pregnancy test first.
Choose a pass for AMC MCQ
Practise Womens Health and every other blueprint domain. One exam per pass, from $30, no auto-renewal.
How to study AMC obstetrics and gynaecology MCQs in our question bank
Women's health has a smaller share of questions than medicine or surgery. It is also dense with numbers that are easy to memorise and easy to confuse.
- Build a gestation timeline: write each test, vaccine and decision against the week it applies, then drill it in the question bank in tutor mode.
- Drill screening results: run every cervical screening outcome until the next step is automatic.
- Practise emergencies under time: PPH, eclampsia, ectopic pregnancy and severe hypertension, at 84 seconds per question.
- Review across domains: pregnancy-related items overlap with the adult medicine hub, and neonatal questions sit in child health.
- Test in mixed blocks: about one item in eight should be women's health, as in the real exam.
For the full list of Australian screening and immunisation differences across domains, see Australian guidelines for the AMC MCQ.
Worked practice questions
A 33-year-old woman has a self-collected Cervical Screening Test. The result shows oncogenic HPV (not types 16 or 18) detected. Her previous screening test five years ago was normal. She has no symptoms and is not pregnant. Which of the following is the most appropriate next step?
- Refer her directly for colposcopy within 8 weeks
- Repeat the self-collected HPV test in 5 years
- Repeat the self-collected HPV test in 12 months
- Arrange a LLETZ procedure without colposcopy
- Recall her for a clinician-collected LBC sample
Show answer and explanation
Answer: E. When HPV (not 16/18) is detected on a self-collected sample, the laboratory cannot perform reflex liquid-based cytology. She must return for a clinician-collected LBC sample to set her risk category. A is the pathway for HPV 16/18 or high-grade cytology. B treats a positive test as negative. C applies only after cytology has placed her at intermediate risk. D is wrong because treatment is never given without colposcopic assessment.
A 31-year-old woman in her second pregnancy attends a routine antenatal visit at 30 weeks' gestation. She received a dTpa vaccine during her first pregnancy 2 years ago, and an influenza vaccine at 12 weeks in this pregnancy. She is well and has no contraindications to vaccination. Which of the following is the most appropriate vaccination advice today?
- dTpa and RSV vaccine (Abrysvo) today
- dTpa only, as RSV vaccine is not yet due
- RSV vaccine only, as dTpa was recent
- A second influenza dose plus dTpa today
- No vaccines until after the baby is born
Show answer and explanation
Answer: A. Pertussis vaccine is recommended in every pregnancy, ideally at 20–32 weeks, regardless of a dose in a previous pregnancy. At 30 weeks she is also within the RSV maternal vaccine window, which starts at 28 weeks and is preferably given by the end of 36 weeks. B is wrong because at 30 weeks she is already inside the RSV vaccine window. C is wrong because dTpa is needed in every pregnancy. D is wrong because only one influenza dose is needed in a pregnancy. E withholds recommended vaccines and loses protection for the newborn.
Sit a timed AMC MCQ mock exam
Blueprint-weighted questions under exam timing, then a breakdown of your result by domain.
Frequently asked questions
How many women's health questions are in the AMC MCQ?
Women's health is 12.5% of the blueprint, so about 19 of the 150 questions cover obstetrics and gynaecology. Because some items are unscored pilot questions, the exact number that counts varies and cannot be identified.
Which Australian guidelines matter most for AMC obstetrics and gynaecology?
The National Cervical Screening Program guidelines, the Australian Immunisation Handbook, Australian Rh D immunoglobulin guidance, SOMANZ hypertension in pregnancy guidance, ADIPS gestational diabetes recommendations and the RACGP preventive care guidance for antenatal visits.
Do AMC women's health questions include breast and sexual health?
Sexual health, contraception and screening commonly appear in women's health stems. Breast lumps are usually assessed with the surgical triple test, so revise them alongside the adult surgery domain as well.
Is the RSV vaccine in pregnancy tested in the AMC MCQ?
Any current Australian recommendation can be tested. The Immunisation Handbook recommends one dose of Abrysvo from 28 weeks, preferably by the end of 36 weeks, in each pregnancy, so it is worth knowing alongside pertussis and influenza timing.
How should I revise obstetrics if I have not practised it recently?
Start with a gestation timeline of routine care, then add emergencies such as PPH, eclampsia and ectopic pregnancy. Practise questions in tutor mode first, then timed. Many IMGs improve quickly here because the content is rule-based.
Are the gestational diabetes thresholds in the exam the old or new ones?
The ADIPS 2025 consensus raised the diagnostic thresholds, and services are adopting them at different speeds. Learn both sets, read the values given in the stem carefully, and choose the answer that is safe under current Australian guidance.